
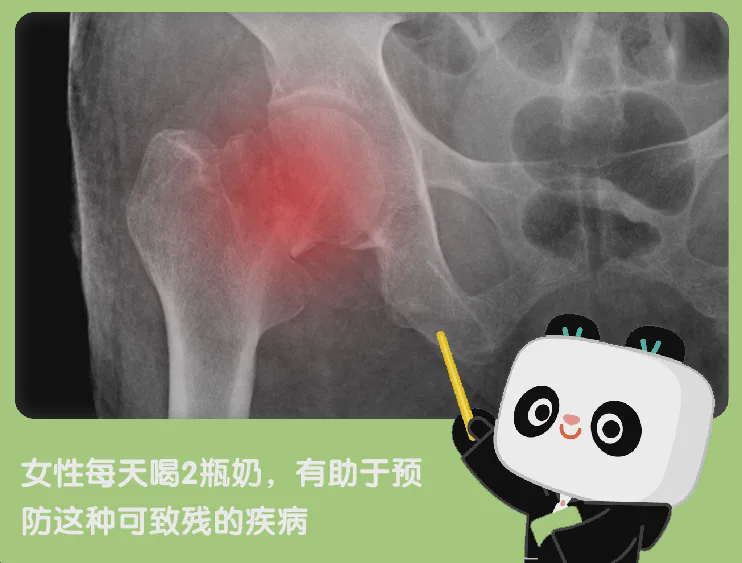
This condition, which can easily cause disability, is called ‘postmenopausal osteoporosis’.
Bones can quietly become brittle like worm-eaten wood, until one day, a fall, a sprained ankle, or even a sneeze causes a fracture.
And this ‘worm damage’ often began as early as our thirties or forties, and there may be no obvious symptoms until a fracture occurs.
If you are in this age group, it is recommended that you do one small thing every day—drink two cups of milk.
After Age 30, Pay Attention to Protecting Your ‘Bone Reserves’
Many people think osteoporosis is an ‘old-age disease’ and has nothing to do with them. But in fact, our bone mass already peaks at around age 30—bone mass reaches its lifetime maximum around age 30 and then begins to decline slowly [1-2].
However, the rate of loss differs from person to person; common influencing factors include:
- Insufficient intake of calcium, vitamin D, and protein: This weakens bone-matrix synthesis and mineralisation, reduces intestinal calcium absorption, and raises parathyroid hormone levels, thereby accelerating bone loss [3-5].
- Smoking: Smoking disrupts bone homeostasis and accelerates bone loss [6].
- Excessive alcohol consumption (at least 3 drinks per day): Oxidative stress from acetaldehyde inhibits osteoblast function and induces apoptosis.
- Genetics: Peak bone mass and the rate of bone loss are regulated by multiple genes, and a parental history of hip or spinal fracture is an important independent risk factor for osteoporosis [2].
But the most critical factor that presses the accelerator on bone loss is a decline in oestrogen levels.
Our bones are in fact constantly ‘replacing the old with the new’—some cells break down old bone while others build new bone, and the two are normally basically balanced. Oestrogen is like the ‘regulator’ that maintains this balance [7-8].
During perimenopause and after menopause, oestrogen decreases substantially, and the speed of ‘bone breakdown’ clearly exceeds that of ‘bone building’, so bones begin to run a deficit [7]. Bone loss is especially rapid during this period: before menopause, only about 0.13% is lost each year, whereas in early menopause it can reach as high as 2.5% per year, nearly 20 times faster [1].
For many women, loss begins to accelerate from around the age of 45, during perimenopause, and is especially rapid in the first five years after menopause [9].
Why Can Osteoporosis Cause Disability?
Hip fracture in women is one of the most serious consequences of postmenopausal osteoporosis and is also called ‘the last fracture of life’. This is a fracture that occurs at the upper end of the femur near the hip joint, usually after a fall [10].
What is frightening about hip fracture is its high rate of disability: after the fracture, it is difficult to regain the ability to care for oneself.
A review article on ‘postmenopausal osteoporosis’ published in The New England Journal of Medicine (NEJM) in 2023 noted that many women are never again able to regain the ability to care for themselves after hip fracture; approximately 20% need to enter nursing institutions, and the risk of death within one year doubles [11].
After a fracture, long-term bed rest is needed; people cannot walk or attend to their own daily needs and therefore need to enter nursing institutions.
For older adults, long-term bed rest itself is also very dangerous.
- Pneumonia after bed rest: When a person cannot walk for a long time, breathing becomes shallow and the airflow into and out of the lungs is reduced; phlegm cannot be moved toward the throat as usual, accumulates increasingly in the lungs, and triggers pneumonia [12]. Many older adults not only have weaker immunity but also underlying conditions such as hypertension, diabetes, chronic obstructive pulmonary disease, and kidney disease, and can easily progress to severe pneumonia or even develop sepsis and respiratory failure [12].
- Deep vein thrombosis of the lower limbs: If leg muscles cannot squeeze blood toward the heart as they did before, blood flows increasingly slowly in the deep veins of the legs, clotting substances easily accumulate, and older adults have poorer blood-vessel conditions, making blood clots more likely [13]. If a clot dislodges, it may travel with the bloodstream to the lungs and block a pulmonary blood vessel, causing ‘pulmonary embolism’ [14].
The global median one-year mortality rate after hip fracture is about 22%; about 20.1% of patients require care in long-term care institutions, and only 42%–71% regain their basic pre-fracture activities of daily living six months after surgery.
A review published in JAMA in 2026 noted that the global median one-year mortality rate after hip fracture is about 22%; about 20.1% of patients require care in long-term care institutions, and only 42%–71% regain their basic pre-fracture activities of daily living six months after surgery [15].
In other words, a hip fracture may be the turning point for an older person from ‘being able to care for oneself’ to ‘being bedridden, or even losing one’s life’.
Bone Mineral Density Testing
This test can identify bone-mass problems before a fracture occurs. Early intervention can slow bone loss and reduce the risk of future fractures.
Testing method: dual-energy X-ray absorptiometry (DXA), which is somewhat like taking an X-ray; radiation exposure is low, and it is completed in a few minutes. The lumbar spine and hip are usually measured; if these sites cannot be measured, the distal one-third of the radius in the forearm can be measured instead.
According to the Chinese Guidelines for the Prevention and Treatment of Osteoporosis, the key groups recommended for bone mineral density testing are:
- Women aged 65 and above and men aged 70 and above;
- Postmenopausal women under 65 and men under 70 with at least one risk factor (such as a history of fragility fracture, parental history of hip fracture, low body weight/low BMI, smoking, excessive alcohol consumption, long-term glucocorticoid use, etc.);
- People of any age with a history of fragility fracture;
- People with imaging findings suggestive of reduced bone mass or the presence of vertebral fracture;
- People who have taken glucocorticoids or other medications affecting bone metabolism for a long time (more than 3 months);
- People with diseases that can cause secondary bone loss (hyperparathyroidism, hyperthyroidism, rheumatoid arthritis, diabetes, chronic kidney disease, malabsorption, etc.).
Why Is It Recommended to Drink Two Cups of Milk Every Day?
The 2015 China Nutrition Transition Cohort Study (approximately 12,000 adults aged 18 to 64) showed that the median dietary calcium intake for the whole population was 328 mg/day, 94.3% did not meet the estimated average requirement, and dairy products contributed only 6.7% of total calcium [16].
That is to say, many people actually consume only a little over 300 mg of calcium each day; for those who hardly drink milk, the gap is even more obvious.
According to the Chinese Dietary Reference Intakes (2023 edition), the recommended daily calcium intake for adults in China is 800 mg [17].
To estimate daily calcium intake, there is a simple clinical method of estimation: ‘a fixed baseline from non-dairy foods plus added dairy products’:
- Do not calculate the calcium content of non-dairy foods separately: directly assume that about 300 mg of calcium per day is obtained from foods such as vegetables, grains, and soy products;
- Add dairy products: most dairy products list their calcium content, making it easy to calculate. If you usually drink milk or yoghurt every day, you can also use the table below to quickly estimate the calcium obtained from dairy.
| Dairy product | Amount per bottle/cup | Calcium content per bottle/cup |
| Milk | 250 ml | 250–300 mg |
| Yoghurt | 100 g | 90–100 mg |
*For estimation only; differences exist among products.
Two bottles of milk contain approximately 500 mg of calcium. Then, 300 plus 500 is approximately 800 mg, reaching the recommended daily amount.
The Chinese Dietary Guidelines (2022) recommend that adults consume 300–500 g of liquid milk or an equivalent amount of dairy products every day. If you cannot drink two bottles of milk, you can replace it with yoghurt, which is convenient to buy, drink, and calculate its calcium content.
Although drinking milk cannot guarantee that we will never fracture a bone in our lifetime, after all, fractures are influenced by many factors. But consuming enough dairy products helps maintain bone mineral density and slow excessively rapid loss of bone mineral density. Bone mineral density is precisely the key to whether bones are strong; if bone mineral density is preserved, the risk of future fractures naturally decreases accordingly.
In addition, you can check whether you have any of these ‘signals that need early attention’ [18-19]:
- Early menopause or premature decline in ovarian function;
- Long-term use (more than 3 months) of glucocorticoids or other medications affecting bone metabolism;
- Smoking or frequent heavy alcohol consumption (such as ≥3 drinks per day);
- Insufficient intake of calcium or vitamin D;
- A mother or close relative with osteoporosis or a history of hip fracture.
If one or more of these apply to you, you can see a doctor in person and have the doctor assess whether you need a bone mineral density assessment earlier.
References
[1] Lobo RA, Gompel A. Management of Menopause: A View Towards Prevention. Lancet Diabetes Endocrinol. 2022.
[2] Morin SN, Leslie WD, Schousboe JT. Osteoporosis: A Review. JAMA. 2025.
[3] Agarwal SC. What is normal bone health? A bioarchaeological perspective on meaningful measures and interpretations of bone strength, loss, and aging. Am J Hum Biol. 2021.
[4] Peris CH, Selvam S, Swaminathan S, et al. Associations of bone health biomarkers and bone mineral density with dietary intakes in vitamin D deficient women: a cross-sectional study. Sci Rep. 2025.
[5] Rizzoli R, Biver E, Brennan-Speranza TC. Nutritional Intake and Bone Health. Lancet Diabetes Endocrinol. 2021.
[6] Kiyota Y, Muramatsu H, Sato Y, et al. Smoking cessation increases levels of osteocalcin and uncarboxylated osteocalcin in human sera. Sci Rep. 2020.
[7] Walker MD, Shane E. Postmenopausal Osteoporosis. N Engl J Med. 2023.
[8] Stokes G, Herath M, Samad N, Trinh A, Milat F. ‘Bone Health—Across a Woman’s Lifespan’. Clin Endocrinol (Oxf). 2025.
[9] Ho-Pham LT, Nguyen HG, Nguyen-Pham SQ, et al. Longitudinal Changes in Bone Mineral Density During Perimenopausal Transition: The Vietnam Osteoporosis Study. Osteoporos Int. 2023.
[10] Handoll HHG, Cameron ID, Mak JC, et al. Multidisciplinary rehabilitation for older people with hip fractures. Cochrane Database of Systematic Reviews, 2021.
[11] Walker MD, Shane E. Postmenopausal Osteoporosis. New England Journal of Medicine, 2023.
[12] Yu Y, Zheng P. Determination of risk factors of postoperative pneumonia in elderly patients with hip fracture: What can we do? PLoS One, 2022.
[13] Cong Y, Wang B, Fei C, et al. Dynamic observation and risk factors analysis of deep vein thrombosis after hip fracture. PLoS One, 2023.
[14] Johannesdottir F, Roberts JE, Kiel DP, Tsai JN. Hip Fractures: A Review. JAMA, 2026.
[15] Johannesdottir F, Roberts JE, Kiel DP, Tsai JN. Hip Fractures: A Review. JAMA. 2026;336(6):496–507. doi:10.1001/jama.2026.11895
[16] Huang F, Wang Z, Zhang J, et al. Dietary Calcium Intake and Food Sources Among Chinese Adults in CNTCS. PLoS One. 2018.
[17] Wei J, Wang J. Chinese residents' knowledge about and behavior towards dairy products: a cross-sectional study. BMC Public Health. 2023.
[18] US Preventive Services Task Force, Curry SJ, Krist AH, et al. Screening for Osteoporosis to Prevent Fractures: US Preventive Services Task Force Recommendation Statement. JAMA. 2018;319(24):2521–2531.
[19] Walker MD, Shane E. Postmenopausal Osteoporosis. N Engl J Med. 2023;389(21):1979–1991.
Disclaimer & Credits
This article was initially drafted with AI assistance, refined by our editorial team, and finalised following professional review by Distinct Healthcare physicians.
This is original content by Distinct Healthcare, provided for informational purposes only and not intended as medical advice. For personalised guidance, please consult a qualified physician.
Contact: health_content@distincthealth.com
Produced by: Distinct Healthcare · Health Express Team
Editorial: Health Express Editorial Team
Medical Review: Distinct Healthcare Physician Team